
What Is a Spinal Tumour?
For educational purposes only. Individual outcomes vary. Not a substitute for personal medical advice.
A spinal tumour is an abnormal growth of cells in or around the spinal cord, its covering (the dura), the nerve roots or the bones of the spine. It can be benign (not cancer) or malignant (cancer), and it can start in the spine (primary) or spread there from a cancer elsewhere in the body (secondary). Its symptoms come mainly from pressure on the spinal cord and nerves.
The spinal cord runs down a protective canal formed by the vertebrae. It is wrapped in a tough membrane, the dura, and bathed in spinal fluid. Nerve roots leave the cord at every level to supply the arms, chest, abdomen, legs, bladder and bowel. A tumour anywhere in this system can press on these structures and cause pain, numbness, weakness or loss of control. Spinal tumours make up about 15–20% of all brain and spinal cord tumours.
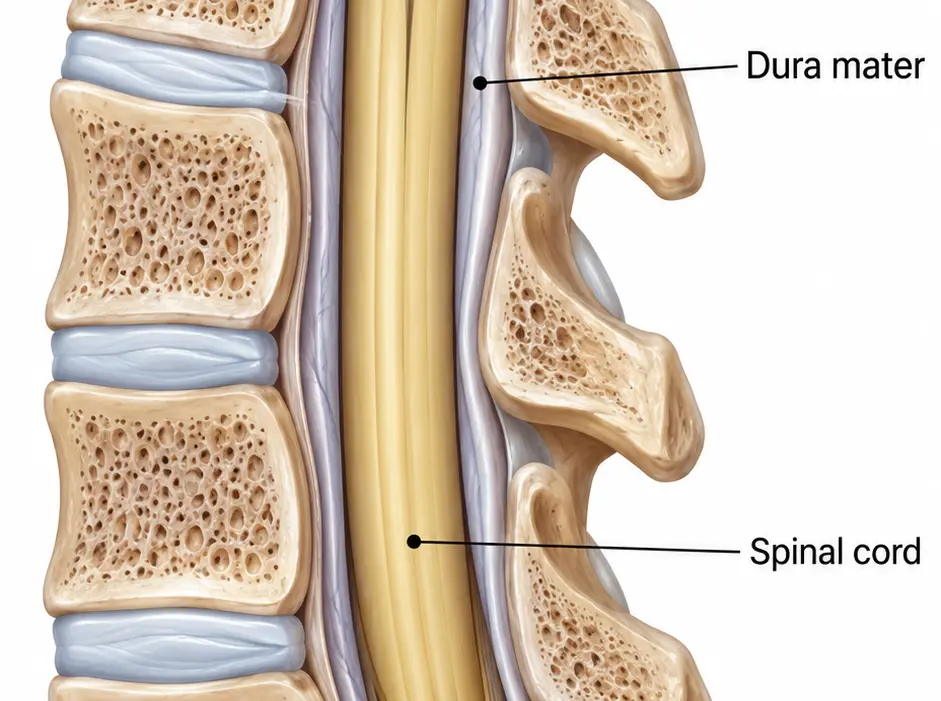
Primary Spinal Tumours
A primary spinal tumour starts in the spine itself — in the spinal cord, its covering, a nerve root or the bone. Common examples are meningioma and schwannoma, ependymoma and astrocytoma inside the cord, and chordoma in the bone. Many primary spinal tumours are benign; the lifetime risk of a malignant primary spinal tumour is under 1%.
Secondary (Metastatic) Spinal Tumours
A secondary spinal tumour, or metastasis, has spread to the spine from a cancer elsewhere — most often the breast, lung, prostate, kidney or thyroid, or from myeloma or lymphoma. In adults these are the commonest spinal tumours. They usually start in the bone of the spine and can press on the cord. Treatment combines radiotherapy, cancer treatment and, when the cord is compressed, tumour removal surgery.
Benign Spinal Tumours
A benign spinal tumour is not cancer: it does not spread to other parts of the body. It can still cause serious problems by pressing on the spinal cord or nerves as it slowly grows. Meningiomas, schwannomas, neurofibromas and vertebral haemangiomas are benign, and many benign tumours can be removed completely by surgery.
Malignant Spinal Tumours (Spine Cancer)
A malignant spinal tumour is cancerous: it can invade nearby tissue and spread. Most are secondaries from a cancer elsewhere. Less often a cancer starts in the spine itself, such as chordoma or a high-grade tumour of the spinal cord; myeloma and lymphoma can also involve the spine. So "spinal tumour" and "spine cancer" are not the same thing.
Types of Spinal Tumour
Neurosurgeons also group spinal tumours by where they lie in relation to the dura (the cord's covering) and the spinal cord. This predicts the likely tumour type, the goal of treatment and the risk of surgery.
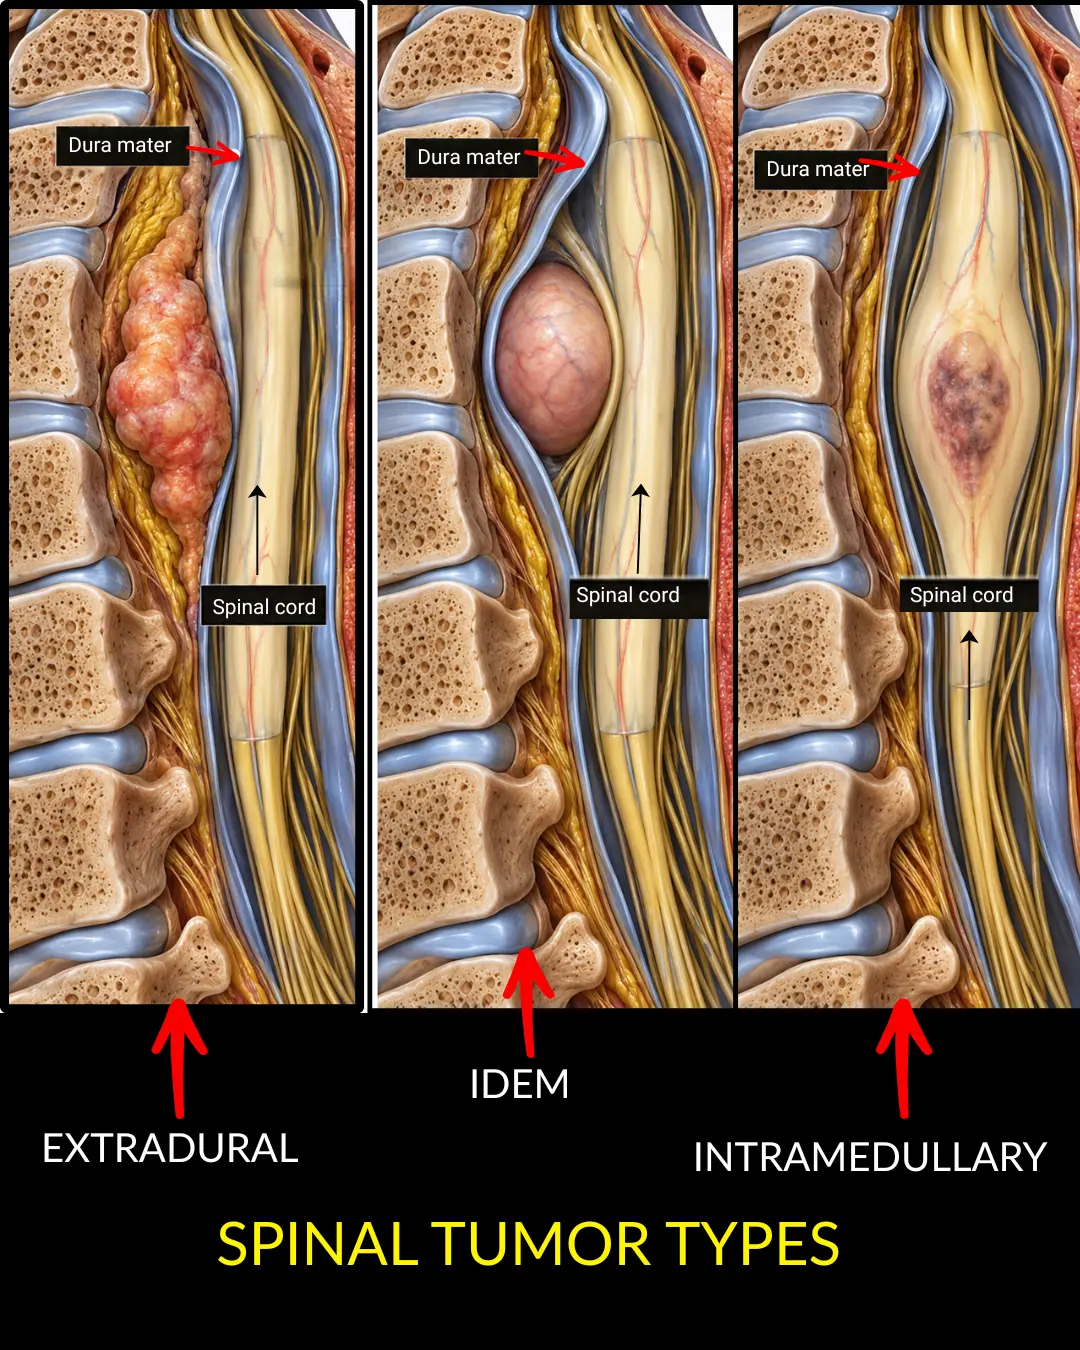
Extradural Tumours
The commonest location. Usually in the bone that surrounds the spinal cord (the vertebra). Most are metastases (secondaries) from breast, lung, prostate, kidney or thyroid cancer, or myeloma and lymphoma. Primary bone tumours such as chordoma are rarer. Treatment may combine radiotherapy, spinal tumour removal surgery and stabilisation. See also vertebral body tumours.
Intradural Extramedullary (IDEM)
Usually benign: meningioma, schwannoma, neurofibroma, and myxopapillary ependymoma at the lower end of the cord. They push the cord aside rather than invading it, so complete removal is often possible. Read about spinal IDEM tumour removal.
Intramedullary Tumours
Grow within the spinal cord itself: ependymoma (commonest in adults), astrocytoma (commonest in children) and haemangioblastoma. The most delicate to treat, needing microsurgery with nerve monitoring. Read about surgery for tumours inside the spinal cord.
| Type | Where It Lies | Common Tumours | Typical Main Treatment | Detailed Page |
|---|---|---|---|---|
| Extradural | Bone around the spinal cord (vertebra) and tissues outside the dura | Usually malignant in adults: metastases, myeloma, lymphoma. Less often chordoma, or a benign haemangioma | Radiotherapy or radiosurgery, separation surgery, stabilisation, cancer treatment | Spinal tumour removal · Vertebral body tumours |
| Intradural extramedullary (IDEM) | Inside the dura, outside the cord | Usually benign: meningioma, schwannoma, neurofibroma | Microsurgical removal, often complete; observation if small and silent | Spinal IDEM removal |
| Intramedullary | Inside the spinal cord | Mostly low-grade, some malignant: ependymoma, astrocytoma, haemangioblastoma | Microsurgical removal with neuromonitoring; radiotherapy for some | Spinal tumour removal |
What Are the Symptoms of a Spinal Tumour?
Symptoms depend on the tumour's level and location, and on how fast it grows. Benign tumours often cause symptoms that build up slowly over months; metastases can cause rapid change over days or weeks.
- Back or neck pain — the commonest first symptom. Typically persistent, gradually worsening, and worse at night or when lying down.
- Radiating pain — a band of pain around the chest or abdomen, or pain down an arm or leg, when a nerve root is involved.
- Numbness and tingling — in the hands, legs or trunk, sometimes with a level on the body below which sensation feels different.
- Weakness — clumsy hands, dropping things, heavy or stiff legs, difficulty climbing stairs.
- Unsteady walking — poor balance, especially in the dark.
- Bladder, bowel or sexual changes — urgency, hesitancy, incontinence, constipation or erectile difficulty.
| Level of the Tumour | Symptoms Patients Commonly Notice |
|---|---|
| Neck (cervical) | Neck pain, pain or numbness in the arms, clumsy hands, difficulty with buttons or writing, stiff legs. The pattern can resemble cervical myelopathy from spondylosis. |
| Mid-back (thoracic) | Mid-back pain, band-like pain around the chest, numbness from the chest or abdomen downwards, leg weakness and unsteadiness. The thoracic spine is a common site for meningiomas and metastases. |
| Lower back (lumbar and sacral) | Low back pain, leg pain resembling sciatica, numbness in the legs or saddle area, weak feet, bladder and bowel changes. |
New or rapidly worsening weakness in the arms or legs, numbness spreading up the body, or new loss of bladder or bowel control can mean the spinal cord is being compressed — especially in someone known to have cancer. Go to the nearest hospital emergency department without delay. UK NICE guidelines recommend whole-spine MRI within 24 hours in this situation.
Is My Back Pain a Spinal Tumour?
This is one of the commonest questions patients ask. The reassuring answer is that the great majority of back and neck pain comes from discs, joints and muscles — conditions such as a slipped disc, spondylosis or canal stenosis — not from a tumour. Certain features, however, call for a medical review, usually an MRI, and an experienced neurosurgeon's opinion.
| Feature | Ordinary Mechanical Back Pain | Pain That Needs Investigation |
|---|---|---|
| Time of day | Worse with activity, eases with rest | Worse at night or lying down; wakes you from sleep |
| Course | Settles over days to a few weeks | Keeps progressing over weeks despite rest and treatment |
| Location | Usually low back or neck | Mid or upper back, or band-like pain around the chest |
| Background | Strain, posture, lifting | Past or current cancer, unexplained weight loss, fever, age over 50 with new pain |
| Nerve symptoms | None, or settle with the pain | Spreading numbness, weakness, clumsy hands, unsteady walking, bladder change |
In someone with cancer, pain alone — severe or progressive back pain, night pain, pain on straining or localised spinal tenderness — is itself a reason for urgent assessment, even before nerve symptoms appear.
What Causes a Spinal Tumour?
For most tumours that start in the spine, no cause is found. A few factors are known to raise the risk:
- A history of cancer — the most important risk factor for spinal metastases. Breast, lung, prostate, kidney and thyroid cancers, myeloma and lymphoma most often spread to the spine.
- Neurofibromatosis type 1 and type 2 — inherited conditions associated with neurofibromas, schwannomas, meningiomas and ependymomas. NF2 is also linked with acoustic schwannoma in the brain.
- Von Hippel–Lindau disease — associated with haemangioblastomas of the spinal cord and brain.
- Previous radiation to the spine, rarely.
Spinal tumours are not caused by injury, lifting or poor posture, and a primary spinal tumour is not the result of anything a patient did.
How Is a Spinal Tumour Diagnosed?
- 1
History and neurological examination — the pattern of pain, numbness and weakness points to the level of the problem. Reflexes, power, sensation and walking are tested.
- 2
MRI with contrast — necessary for diagnosis. It shows the tumour, exactly where it lies, its relation to the cord and nerves, and any swelling or cyst within the cord. When metastasis is suspected, the whole spine is scanned.
- 3
CT scan — shows bone destruction, calcification and whether the spine is stable. It is also used to plan screws and rods.
- 4
Whole-body imaging — CT of the chest, abdomen and pelvis, or PET-CT, when the tumour may have come from a cancer elsewhere.
- 5
Blood tests — general health, and markers for conditions such as myeloma or prostate cancer when relevant.
- 6
Biopsy — usually a CT-guided needle biopsy, when the diagnosis is uncertain and it would change treatment.
What Do the Terms in a Spinal Tumour MRI Report Mean?
- Extradural
- Outside the dura, the covering of the spinal cord
- Intradural extramedullary (IDEM)
- Inside the dura, but outside the spinal cord
- Intramedullary
- Inside the spinal cord itself
- Enhancing lesion
- An area that lights up with contrast dye
- Cord compression
- The spinal cord is being squeezed
- Cord oedema
- Swelling of the spinal cord
- Syrinx
- A fluid-filled cavity inside the cord
- Dural tail
- A feature typical of meningioma
Bring the MRI images, not only the report, to your consultation.
What Is the Treatment for a Spinal Tumour?
For educational purposes only. Treatment is individual and is decided after examination and review of your scans.
Observation
Small benign tumours that cause no symptoms — often found by chance on an MRI done for something else — may be watched with periodic MRI. Treatment is considered if the tumour grows or symptoms appear.
Surgery
To remove the tumour, relieve pressure on the cord and nerves, obtain a diagnosis, and stabilise the spine when needed. See spinal tumour removal and resection and removal of meningiomas and schwannomas.
Radiotherapy and Radiosurgery
Conventional radiotherapy, or stereotactic radiosurgery (SBRT) that delivers high doses precisely to the tumour while sparing the cord. Used alone for many metastases, or after surgery.
Cancer Treatment and Steroids
Chemotherapy, hormone, targeted or immunotherapy for the original cancer. Steroids such as dexamethasone may be given urgently to reduce swelling around a compressed cord.
| Situation | Usual Aim of Treatment | Common Approach |
|---|---|---|
| Benign IDEM tumour (meningioma, schwannoma) causing symptoms | Complete removal, which is often curative | Microsurgical IDEM tumour removal with neuromonitoring |
| Intramedullary tumour (ependymoma, astrocytoma) | Maximum safe removal while preserving function | Microsurgery with neuromonitoring; radiotherapy for some types |
| Metastasis compressing the cord | Protect walking and bladder control, relieve pain, keep the spine stable | Separation surgery and stabilisation followed by radiotherapy or radiosurgery, plus cancer treatment |
| Metastasis without cord compression or instability | Pain relief and local tumour control | Radiotherapy or radiosurgery and cancer treatment; surgery not always needed |
| Unstable or collapsed vertebra | Restore stability and relieve pain | Spinal instrumentation with screws and rods, sometimes cement augmentation |
For benign tumours, surgery usually aims at complete removal and cure. For metastases, the aim is usually to protect the spinal cord, relieve pain and keep the spine stable, alongside treatment of the cancer itself. Decisions for metastases weigh four things: the neurological state, how sensitive the tumour is to radiation, the stability of the spine, and the patient's overall health and cancer outlook.
How Is Spinal Tumour Removal Surgery Performed?
Generally, spinal tumour surgery is done under general anaesthesia, usually from the back, using an operating microscope. Intraoperative neuromonitoring tracks the function of the cord and nerves throughout, so the surgeon is warned while that area is being handled. The bone at the back of the spine is opened (laminectomy or laminoplasty), and for intradural tumours the dura is opened and later closed watertight.
Spinal Tumour Removal
For tumours inside the cord (intramedullary) and outside the dura (extradural), including metastases: goals of surgery, separation surgery, stabilisation, risks, recovery and follow-up.
Spinal IDEM Tumour Removal
For meningiomas, schwannomas and neurofibromas inside the dura but outside the cord: when surgery is advised, the step-by-step operation, risks and recovery.
When a tumour has weakened the vertebrae, the spine is stabilised at the same operation with spinal instrumentation. Tumours in the mid-back may need thoracic decompression, and some neck tumours are reached by cervical laminectomy.
Is It Possible to Recover from Spinal Tumour Removal Surgery?
Yes — many patients recover well, especially after removal of a benign tumour. Recovery after spinal tumour surgery depends mainly on the type of tumour, how much of it can be removed safely, and how much weakness was present before treatment. Function that is still present before surgery is much more likely to be preserved, which is why early assessment matters. Completely removed benign tumours rarely come back, and follow-up MRI scans are planned after surgery.
Quick answers: How long is recovery? · Will I walk after surgery? · Can it come back? · What is the survival rate?
What Is the Cost of Spinal Tumour Treatment in India?
Patients often search for a single figure, but the cost of spinal tumour treatment varies widely. The main factors are:
- The tumour's location and level, and the length of the operation
- Whether screws, rods or other implants are needed
- Intraoperative neuromonitoring and the operating microscope
- Hospital and room category, length of stay and any intensive care
- Biopsy, pathology and imaging such as MRI, CT or PET-CT
- Radiotherapy, radiosurgery, cancer treatment and rehabilitation afterwards
Ask the hospital for a written estimate before planned surgery and check with your insurer what is covered. Procedure-specific information is on the spinal tumour removal and IDEM tumour removal pages.
Questions to Ask Your Neurosurgeon
- 1
Is my spinal tumour cancerous or benign? — Ask what the MRI suggests, and whether a biopsy is needed to be sure.
- 2
What type of spinal tumour do I have? — Ask exactly where it lies — in the bone, the cord's covering or the cord itself — and what it is most likely to be.
- 3
Does a spinal tumour always need surgery? — Ask whether yours can be watched with repeat MRI, or treated with radiotherapy instead.
- 4
Can a spinal tumour cause paralysis? — Ask whether your spinal cord is at risk while you decide, and which symptoms should bring you back urgently.
- 5
Can the whole spinal tumour be removed? — Ask whether the aim is complete removal, relief of pressure on the cord, or a diagnosis.
- 6
Is spinal tumour surgery risky? — Ask about the main risks in your case, and how nerve monitoring will be used during the operation.
- 7
Will I walk after spinal tumour surgery, and how long is recovery? — Ask about time in hospital, rehabilitation and return to work.
- 8
Will I need screws and rods, radiotherapy or chemotherapy? — Ask which other specialists will be involved in your care.
- 9
Can a spinal tumour come back after surgery? — Ask how often follow-up MRI scans will be done.
- 10
What is the cost of spinal tumour surgery? — Ask for a written estimate, and check what your insurance covers.
Frequently Asked Questions About Spinal Tumours
General information only. Please consult a qualified neurosurgeon or spine surgeon for advice about your situation.
What is a spinal tumour?
Are spinal tumours cancerous? Is a spinal tumour the same as spine cancer?
What are the types of spinal tumours?
What causes spinal tumours?
How fast do spinal tumours grow?
Is a vertebral hemangioma a dangerous spinal tumour?
What are the first symptoms of a spinal tumour?
How do I know if my back pain is caused by a tumour?
Can a spinal tumour be mistaken for a slipped disc or sciatica?
Can a spinal tumour cause paralysis?
Which test detects a spinal tumour? Will an X-ray show it?
Is a biopsy always needed before spinal tumour treatment?
Can spinal tumours be treated without surgery?
Can a tumour inside the spinal cord be removed?
Is a spinal tumour like meningioma or schwannoma cancerous?
What is separation surgery for spinal metastases?
Will I need screws and rods after spinal tumour surgery?
Is spinal tumour surgery risky?
How long is recovery after spinal tumour surgery?
Will I be able to walk after spinal tumour surgery?
Can a spinal tumour come back after surgery?
What is the survival rate for spinal tumours?
How much does spinal tumour surgery cost in India?
Which doctor treats spinal tumours — a neurosurgeon or an orthopaedic spine surgeon?
Who treats spinal tumours in Pune?
Should I get a second opinion for a spinal tumour?
A Note from Dr Jaydev Panchawagh
Most people who come to see me after an MRI shows a spinal tumour arrive frightened, often having read that "tumour" means cancer. The first thing I explain is where the tumour sits — outside the dura, inside the dura but outside the cord, or within the cord itself — because that one fact shapes almost every decision that follows. Many tumours in the middle group, such as meningiomas and schwannomas, are benign and can often be removed completely.
I ask patients and families for two things. First, do not ignore the warning signs: new weakness, numbness rising up the body, or a change in bladder control needs attention the same day. Second, when there is no emergency, do not rush into an operation without understanding its goal, its risks and the alternatives. In most cases a clear plan, made together with an oncologist and a radiation specialist when needed, matters more than speed; in a few, speed matters most. The purpose of the first consultation is to establish which situation you are in.
Dr Jaydev Panchawagh
MS (General Surgery), MCh (Neurosurgery) · Consultant Neurosurgeon, Pune
27 years of independent neurosurgical practice · 3,000+ spine surgeries


